


































About Measles
Measles was declared eliminated from the United States in 2000. On November XXX, 2026, the Pan American Health Organization (PAHO) confirmed what public health officials had long seen coming: the United States had lost that status, becoming the latest country in the Americas to see measles return as an endemic health threat. Canada lost its elimination status earlier in the year, with similar underlying drivers.
More than 3,800 cases have been counted in 2026 alone, making it the worst year for measles infections since the early 1990s. At least two people have died, and ninety-five percent of confirmed cases are outbreak-associated. National vaccination coverage among kindergartners has declined from 95.2% during the 2019-2020 school year to 92.5% in 2024-2025, falling below the 95% threshold required for community protection. Rising vaccine hesitancy and state legislatures loosening school entry requirements have compounded the problem.
For those tracking the data closely, the PAHO decision was a confirmation, not a verdict. “What it confirms is that measles has returned—and that the work of containing it falls, as it always has, on the health departments, epidemiologists and preparedness staff working county by county, outbreak by outbreak, family by family,” says Caitlin Rivers, an infectious disease epidemiologist who leads the Center for Outbreak Response Innovation at Johns Hopkins University.
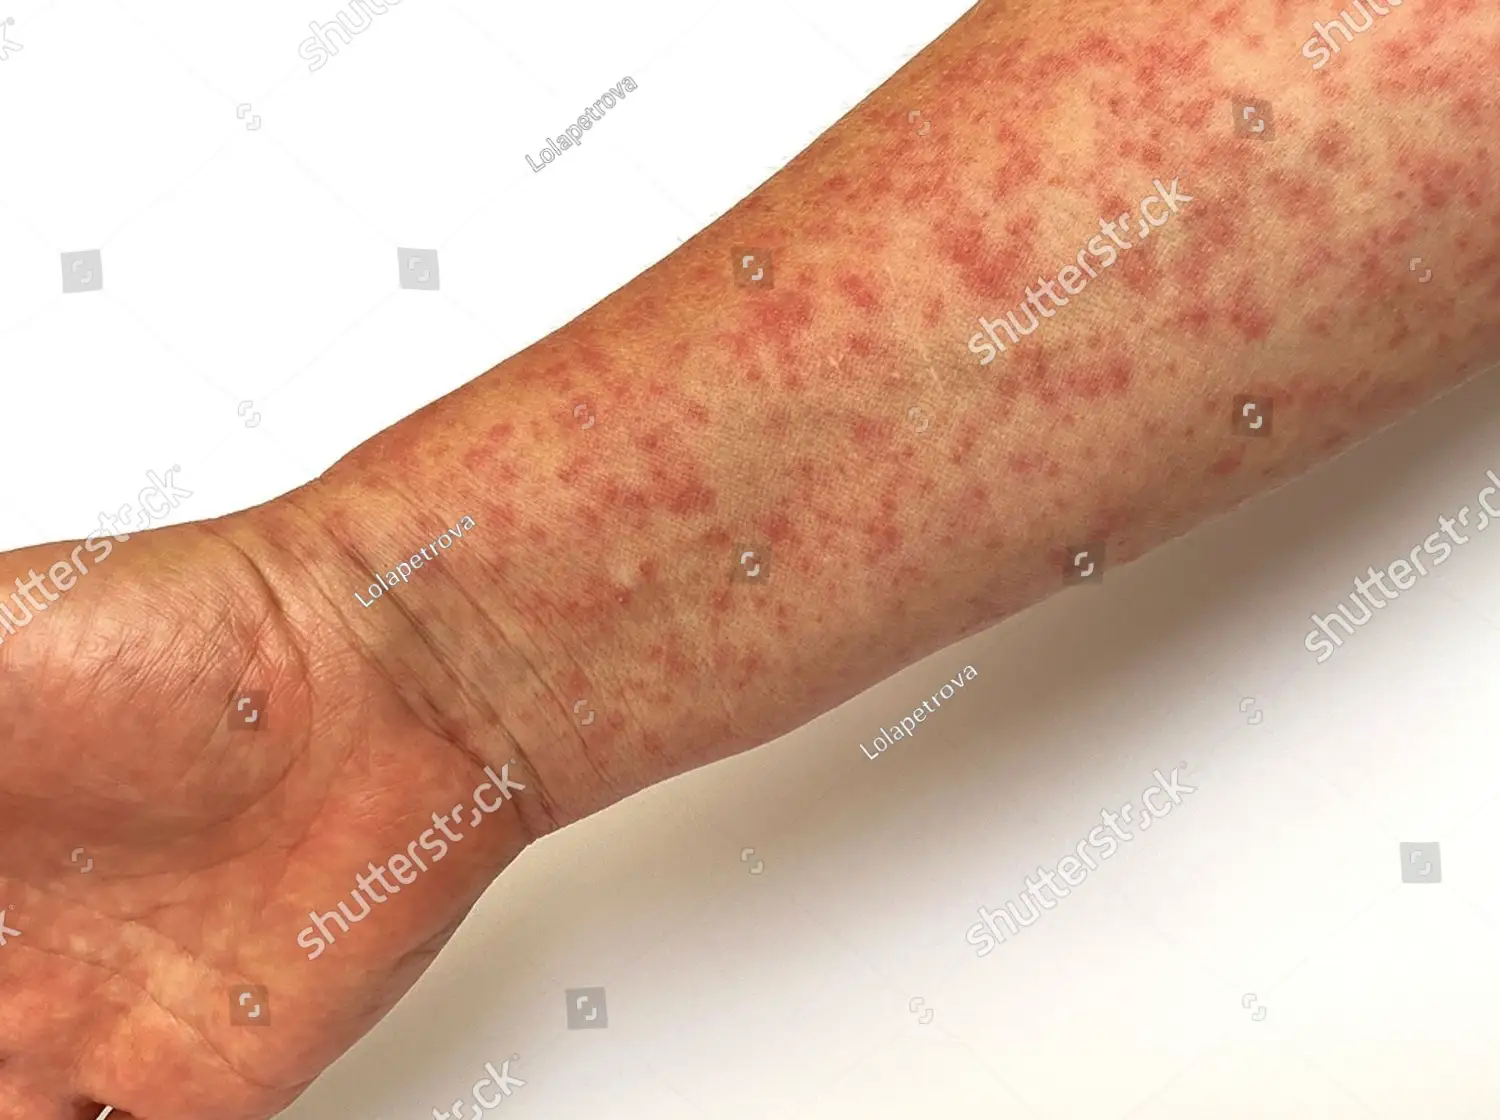
The Center works with state and local health departments to make outbreak responses faster, more effective and less improvised. Working closely with state and local partners, Rivers and her team have developed practical resources to support health departments facing measles cases, including a clinical guide to recognizing the measles rash across different skin tones and a repository of off-the-shelf response materials so that no team has to build everything from scratch.
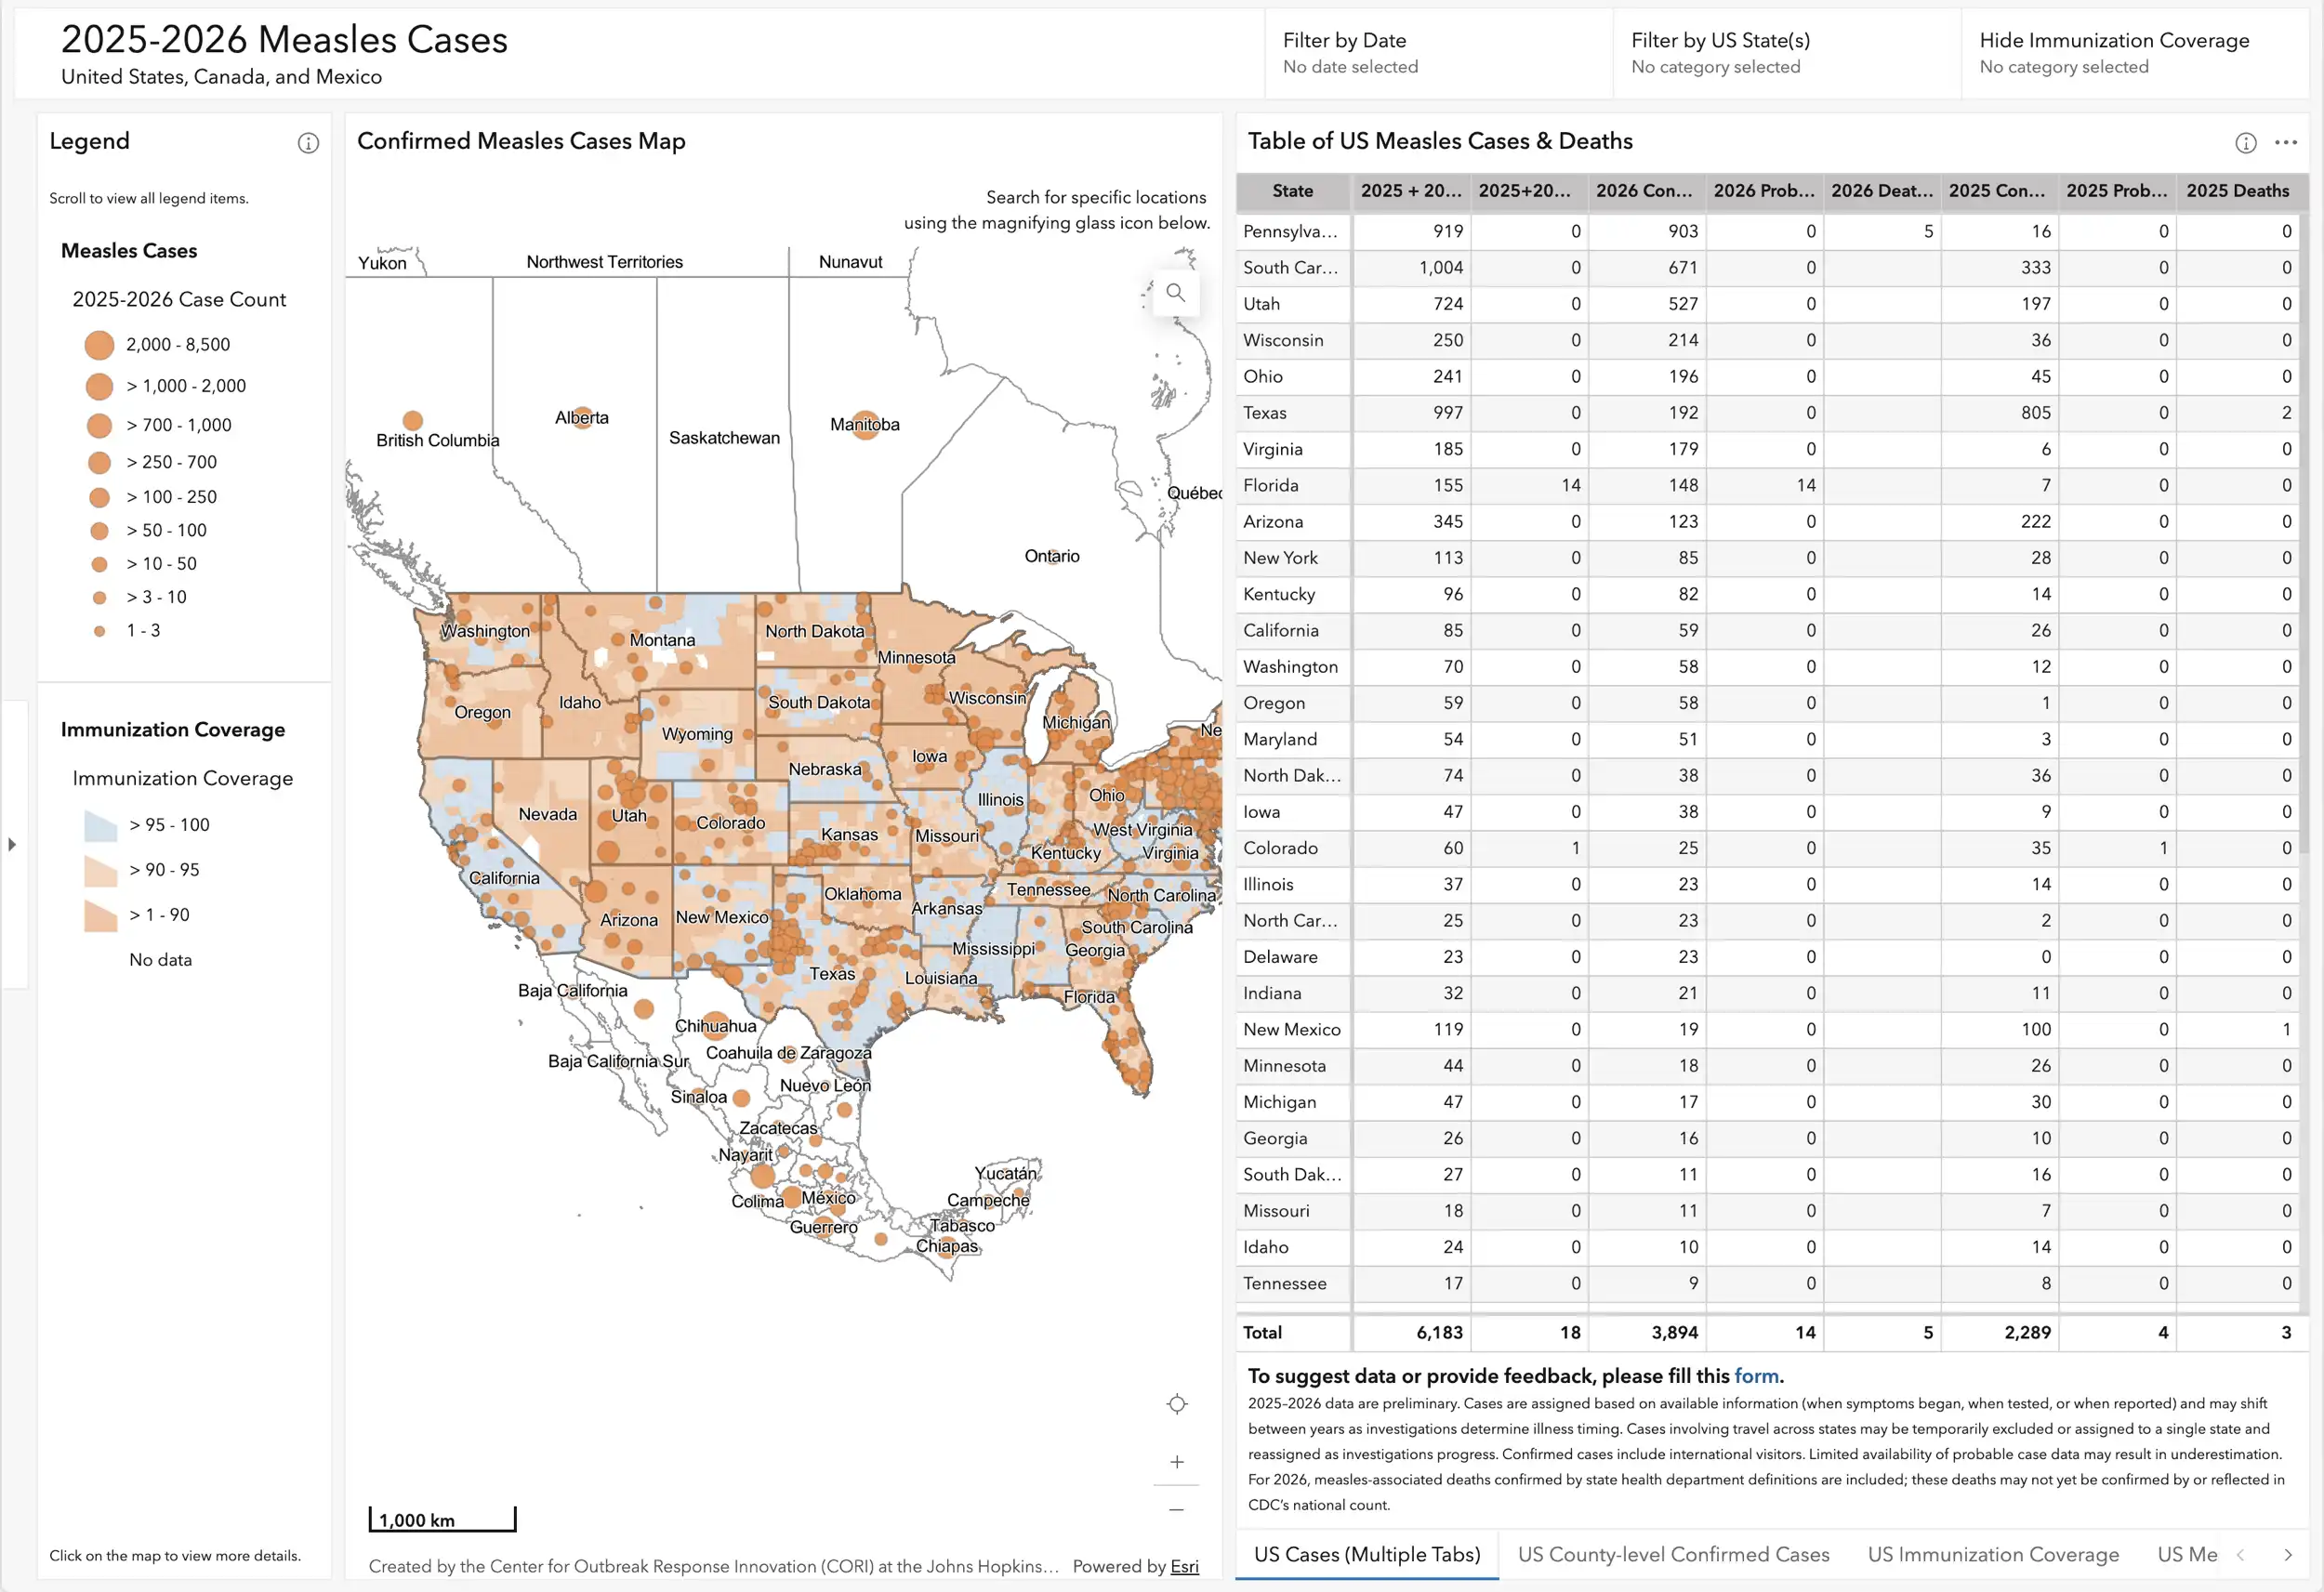
The Center’s now hosts a measles dashboard that tracks cases, public exposure notices and vaccination coverage in closer to real time than CDC’s weekly updates, offering health departments and the public a timely picture of what is happening and where. It also has a formal agreement to collaborate with Resolve to Save Lives, anchored by a shared conviction that the 7-1-7 target fills a gap U.S. public health has long lacked: strong process metrics for outbreak response, not just endpoint measures.
Against a challenging national backdrop, some jurisdictions are beating the trend. In Pima County, Arizona, Mecklenburg County, North Carolina and Tennessee, public health teams have moved fast, kept case counts low and stopped outbreaks before they spiraled into larger problems. “Getting large outbreaks under control is impressive,” says Rivers. “The longer one goes on, the harder it becomes to contain. That effort deserves recognition.”
Three factors set these jurisdictions apart.
Surveillance: The successful teams aren’t waiting for a case to arrive before they start paying attention. They monitor neighboring jurisdictions, join multistate calls and watch wastewater to build a picture of what’s coming their way.
Timeliness: Speed saves lives in measles response. These jurisdictions have embedded the 7-1-7 target, which sets standards for how quickly health departments should detect, notify and respond to an outbreak, into their everyday operations.
Relationships: The jurisdictions doing well invest in relationships between teams, organizations and the communities they serve. Those connections are what allow a vaccine clinic to stand up quickly and a hesitant family to open their door.
The Response
Pima County, Arizona
When the index case was confirmed, Pima’s Chief Medical Officer moved quickly to connect with the health facility where the traveler presented symptoms. Around 210 contacts were traced and monitored. Within days, a vaccine clinic was running outside regular business hours at El Rio Health Congress, a medical center in Tucson, and publicized to residents so they knew where to go. By January 17, just four days after the first case was detected, the health department had completed all its early response actions.
A second case emerged on January 22 and set off the response’s most intense moment. An unvaccinated healthcare worker with direct exposure to the index case developed symptoms. She had since worked in a pediatric setting, and a subgroup of infants, too young to be vaccinated, had been exposed. The team identified eight to 10 such infants, coordinated with state partners and arranged for immunoglobulin to be delivered to El Rio. That night, the team spent hours calling each family to bring their child in the next morning. None of the infants developed measles.
Eleana Acosta Zavala, the epidemiologist who led the response, pointed to two factors critical to Pima’s successful response. “Our leadership has invested in relationships with their counterparts at other organizations long before the outbreak, rather than scrambling to meet people once it had started,” said Acosta Zavala. “We’ve also invested heavily and consistently in maintaining vaccination rates and tracking timeliness metrics.”
Use of 7-1-7
Pima County has been using the 7-1-7 target for around four years, embedding it into outbreak response work that began during COVID-19 and has continued since. “The 7-1-7 target creates space for action items that lead to creative solutions,” said Acosta Zavala. Since January’s outbreak, the team has already put lessons into action: when another measles case arrived in the spring, they stood up a contact tracing call center within a single day, something that had taken considerably longer in previous outbreaks.
Mecklenburg County, North Carolina
Mecklenburg’s response started six months before those first cases arrived. Paige Bennett, Deputy Director of Mecklenburg County Public Health, had been joining weekly calls to track the South Carolina outbreak as it grew. “During that time, our team built relationships with our counterparts in South Carolina,” said Bennett. “We also started working on a new case management system to support contact tracing and expedited vaccination of children who hadn’t yet completed their series.”
When measles appeared in Mecklenburg’s wastewater, the team was ready. Health officials immediately opened walk-in vaccine clinics, before the first cases were confirmed. Once confirmation came, the department activated its Incident Command System and investigators began working through the exposure lists, cross-referencing names against the state immunization registry to identify who was unvaccinated.
For high-risk contacts who lacked protection, the team coordinated with local hospitals to arrange immunoglobulin administration. Public exposure notices went out to affected communities, including event sites, and communications staff fielded questions from residents about what exposure meant, what isolation required and how to get vaccinated.
A third case in an unvaccinated child who lived in Mecklenburg but attended school in neighboring Union County was confirmed on January 27 and handled in close coordination with Union County Public Health. Mecklenburg ended up with 3 confirmed cases and no deaths. By early February, the immediate response was over.
Use of 7-1-7
“For our team, 7-1-7 functions as a quality improvement tool as much as an outbreak metric,” said Bennett. The framework has been embedded into her team’s infectious disease plan, and the after-action review that followed the measles outbreak gave the communicable disease team a reason to connect with community health educators, who previously worked in isolation. “Those relationships can make or break a response effort,” notes Bennett. “They didn’t exist before. And now that they do, they’ll long outlast this particular outbreak.”
Tennessee
A week before families started turning up at the health department’s waiting room, health officials in neighboring Kentucky had shared unconfirmed reports of a potential outbreak on a routine multistate call, where Tennessee health department staff were listening. When Kentucky formally announced its outbreak a few days later, the team immediately shared that information with public health staff and healthcare providers in the affected border areas. Staff were already on high alert when the first families walked through the door.

From there, the response moved quickly. Local and regional staff conducted home visits and community visits, allowing active case finding, vaccination outreach and relationship building at the same time. The health department activated its Incident Command System, bringing together communicable disease and preparedness staff from multiple regions along with laboratory, communications and healthcare-associated infections staff. A community vaccination clinic was set up, and more than 100 contacts were traced, while support was provided to quarantining families.
The pairing of disease expertise and preparedness experience is unusual in U.S. public health, but it’s built into how Tennessee operates. “The two teams sit in the same division and can function side by side when an Incident Command System activates,” said Dr. Mary-Margaret Fill, Tennessee’s state epidemiologist. “The result is a much more effective response effort.”
The success of the response is also attributed to building trust with communities that don’t proactively seek medical care unless they really need it. Part of Tennessee’s response depended on efforts from health officials and nurses building the rapport that made community outreach possible. “In a community that is deeply private, but not opposed to vaccination, empathetic communication makes all the difference,” said Dr. Fill.
Three more cases appeared the week of September 7, all household contacts of one of the initial cases, bringing the total to six. While the outbreak is ongoing, the team anticipates the outbreak stopping with these six cases as they move through the incubation period.
Use of 7-1-7
Tennessee began incorporating 7-1-7 into outbreak reporting requirements in 2024, building the metrics into its existing REDCap data system rather than creating new burden for field staff. Bottleneck and enabler analysis followed in a second phase. “For field staff, applying 7-1-7 never felt like a new thing, which is why it was easy to make it the norm,” said Julie Shaffner, an epidemiologist credited with building 7-1-7 into the state’s routine operations. “We now have a team of ‘timeliness champions’ who think less about hitting specific numbers and more about timeliness as a value embedded in how they work.